

Optimizing Multi-Appointment Medical Scheduling with Genetic Algorithms
Scheduling medical appointments is rarely a simple task. For patients who require multiple examinations across different specialties, the process can become surprisingly complex. Each appointment must align with practitioner availability, equipment constraints, room schedules, and – most critically – clinical safety rules that define how certain procedures interact with one another.
In many healthcare organizations, this complexity is still managed through manual workflows or simple heuristics such as first-come, first-served booking. While these methods work for single appointments, they struggle to efficiently coordinate multi-exam patient journeys across multiple facilities. The result is often fragmented schedules, unnecessary travel, and long waiting periods between appointments.
In our recent research paper, Outpatient Appointment Scheduling Optimization with a Genetic Algorithm Approach, we explored how evolutionary computation can address this challenge.
The Complexity of Multi-Exam Scheduling
Coordinating multiple medical procedures introduces several layers of constraints:
- Clinical incompatibilities – Certain exams require mandatory time gaps to avoid physiological or diagnostic interference.
- Temporal conflicts – Appointments must not overlap and must fit within available time slots.
- Geographical logistics – Exams may occur in different healthcare centers, requiring travel time between facilities.
- Patient experience considerations – Long idle periods between exams can significantly degrade the patient experience.
When these factors interact, the scheduling problem quickly becomes combinatorially complex. As the number of requested exams and available time slots grows, the number of possible scheduling combinations increases exponentially. This places the problem in the class of NP-hard optimization problems, where exact mathematical solutions become computationally impractical at scale.
This is precisely the type of scenario in which metaheuristic optimization methods, such as Genetic Algorithms (GAs), can be highly effective.
A Genetic Algorithm Approach
Genetic Algorithms are inspired by evolutionary processes in nature. Instead of attempting to compute the perfect solution, the algorithm evolves a population of candidate schedules over many iterations, gradually improving their quality through selection, crossover, and mutation.
In our implementation:
- Each candidate solution (individual) represents a full schedule for all requested medical acts.
- Each act is assigned to exactly one available time slot.
- The complete schedule is encoded as a binary chromosome, representing the selected slots.
The algorithm starts with a population of 100 candidate schedules. Each generation undergoes the following steps:
- Fitness evaluation – Each schedule is scored according to constraint satisfaction and patient-centric efficiency metrics.
- Selection – Higher-quality schedules are more likely to be chosen for the next generation.
- Crossover – Portions of two schedules are combined to produce new candidates.
- Mutation – Small random changes introduce diversity and prevent premature convergence.
The process is repeated for 200 generations, gradually pushing the population toward more optimal scheduling solutions.
Modeling Real-World Constraints
To simulate realistic healthcare operations, we generated a synthetic dataset representing:
- 50 medical exams across five specialties
- Four healthcare facilities
- Three examination rooms per facility
- 30 days of scheduling availability
Each exam was associated with randomly generated time slots based on practitioner availability and slot duration. Additionally, we introduced 15 stochastic incompatibility rules between exam pairs, defining required temporal gaps ranging from 30 minutes to 24 hours.
These rules simulate clinical realities such as recovery periods or procedures that may interfere with diagnostic outcomes.
Smart Initialization: Ordered vs. Unordered Populations
We evaluated two different strategies for generating the initial population:
Unordered Initialization
- Exam slots are selected randomly without considering incompatibility relationships.
Pre-Ordered Initialization
- Exams are first arranged in an optimized sequence based on incompatibility rules before slot selection.
The hypothesis was that incorporating domain knowledge during initialization might improve early search efficiency.
Benchmarking Against Traditional Approaches
To evaluate the effectiveness of the Genetic Algorithm, we compared it against two baseline scheduling methods:
- First-Come, First-Served (FCFS) – A deterministic method that assigns the earliest available slot for each exam.
- Random Choice - A stochastic baseline that selects a random valid slot for each exam.
These baselines represent typical real-world booking approaches and provide a reference for measuring optimization gains.
Measuring Scheduling Quality
We evaluated scheduling performance using several patient-centric metrics.
Idle Time Ratio (ITR)
The Idle Time Ratio measures how efficiently appointments are clustered within a patient’s journey.
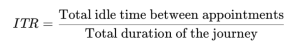
An ITR close to 0 indicates tightly packed appointments with minimal waiting time.
Inter-Facility Displacement
This metric counts the number of required trips between healthcare facilities. Fewer trips generally indicate a more convenient patient journey.
Constraint Violation Rate
Three types of constraints were strictly monitored:
- Temporal overlaps
- Clinical incompatibility violations
- Insufficient travel gaps between facilities
Results
The results showed a clear advantage for the Genetic Algorithm approach.
Perfect Constraint Compliance
Both GA variants achieved 100% compliance with all scheduling constraints, eliminating:
- Overlapping appointments
- Clinical incompatibilities
- Infeasible travel gaps
In contrast, the FCFS approach failed to resolve temporal overlaps in 60% of cases and violated travel constraints in 40% of schedules.
Improved Patient Experience
The GA solutions significantly improved patient-centric metrics:
- Idle Time Ratio frequently below 0.4, compared with values close to 1.0 for baseline approaches.
- Reduced inter-facility travel, with a median of only two required trips.
These improvements were statistically significant (p
Ordered vs. Unordered Initialization
The pre-ordered initialization strategy produced higher initial fitness values, confirming that domain knowledge improves early search performance.
However, both approaches converged to similar optimal solutions after approximately 100 generations, demonstrating the robustness of the evolutionary process.
Figure 1: Mean Fitness Convergence Profiles across 200 Generations. This plot illustrates the evolutionary progression of the GA (Ordered) and GA (Unordered) variants compared to the FCFS and Random Choice baselines.
Implications for Healthcare Operations
These findings suggest that automated scheduling systems based on metaheuristic optimization could significantly improve healthcare operations.
Potential benefits include:
- Strict enforcement of clinical safety constraints
- Reduced administrative workload
- Improved patient experience through shorter wait times
- Fewer inter-facility trips
- Higher appointment conversion rates through optimized scheduling suggestions
Instead of forcing patients or staff to manually assemble complex appointment chains, our intelligent scheduling engine could proactively generate optimized schedules within seconds.
Conclusion
Multi-appointment medical scheduling is a complex optimization problem that traditional manual workflows and simple heuristics struggle to solve efficiently. Our research demonstrates that Genetic Algorithms provide a powerful and scalable approach for navigating this complexity.
By evolving candidate schedules and evaluating them against both clinical and logistical constraints, the algorithm consistently produces solutions that are safer, more efficient, and more patient-friendly.
As healthcare systems continue to digitize and scale, intelligent scheduling frameworks like this could play a key role in transforming fragmented appointment workflows into coordinated patient journeys.
📄 You can read the full research paper here: https://arxiv.org/abs/2602.21995